

Table of Contents
- Clinical Criteria for Resistant Depression
- Medication Augmentation Strategies When First-Line Drugs Fail
- Esketamine Treatment for Depression: What Patients Should Know
- TMS Therapy for Depression: A Non-Invasive Neurostimulation Option
- Other Evidence-Based Treatment Options for Resistant Depression
- A Patient-Centered Recovery Roadmap: From Evaluation to Maintenance
- Caregiver Support and Resources for Families Navigating Refractory Depression
- Conclusion
Last Updated: August 26, 2026
For people who have tried two or more antidepressants at adequate doses without meaningful relief, the clinical term is treatment-resistant depression (TRD). At Salado Creek Mental Health, we work with patients at exactly this point: exhausted by failed medications and unsure where to turn next. This guide covers the full landscape of treatment options, from medication augmentation to neurostimulation to psychotherapy, so you can approach your next psychiatric evaluation with clarity about what’s available.
The field has advanced considerably. Several FDA-approved options now exist that were unavailable a decade ago, and the evidence base for multimodal approaches continues to grow.
Clinical Criteria for Resistant Depression
Treatment-resistant depression is defined as a major depressive episode that has not responded to at least two adequate trials of antidepressant therapy, where "adequate" means the correct dose for six to eight weeks. This definition shapes which interventions are appropriate next steps.
According to [the National Institute of Mental Health(/about-the-clinic/)’s overview of depression | nimh.nih.gov], a substantial subset of patients with major depressive disorder do not achieve full remission with standard first-line pharmacotherapy.
How Treatment-Resistant Depression Differs from Major Depressive Disorder
Major depressive disorder is the broader diagnosis. Resistant depression is a clinical subtype defined by treatment failure, not symptom severity alone. A patient can have relatively mild symptoms and still meet TRD criteria if those symptoms persist through multiple medication trials.
This distinction matters practically. Standard MDD treatment begins with SSRIs or SNRIs. TRD treatment skips those first-line options and moves directly into augmentation, neurostimulation, or interventional psychiatry.
Comorbid Conditions That Complicate Diagnosis
Undiagnosed bipolar disorder, PTSD, ADHD, anxiety disorders, and substance use disorders can all blunt the therapeutic response to standard antidepressants, as can untreated thyroid dysfunction or sleep apnea. A thorough psychiatric evaluation should screen for these conditions before a patient is labeled as having TRD. Treating the comorbidity sometimes resolves what appeared to be refractory depression entirely.
Medication Augmentation Strategies When First-Line Drugs Fail
The most common initial response to antidepressant failure is augmentation: adding a second agent to the existing regimen rather than switching outright. This approach is backed by substantial evidence and remains the standard of care before more intensive interventions.
Common Adjunctive Therapy Combinations
Several adjunctive options have well-established evidence:
- Atypical antipsychotics (aripiprazole, quetiapine, olanzapine) added to an existing antidepressant carry FDA approval for this indication
- Lithium augmentation has decades of evidence, particularly for patients with mood disorder features
- Thyroid hormone (T3) is sometimes added when thyroid function is borderline or other augmentation strategies have failed
- Buspirone is occasionally used as an adjunct for patients with prominent anxiety
- Stimulant medications may be considered when ADHD is a confirmed comorbid condition
The choice depends on the patient’s symptom profile, side effect history, and comorbidities.
Monitoring Side Effect Profiles and Treatment Adherence
A common mistake is attributing treatment failure to the medication when the real issue is inconsistent adherence or an unmanaged side effect. Metabolic effects, sexual dysfunction, weight gain, and sedation are among the most common reasons patients reduce their dose without telling their provider.
Proactive monitoring of side effects at every appointment, combined with honest conversations about adherence, catches these issues early.
Ask your prescriber specifically about the difference between a dose reduction and a medication failure. Many patients tolerate a lower dose better and still achieve meaningful therapeutic response.
Esketamine Treatment for Depression: What Patients Should Know
Esketamine (brand name Spravato) is an FDA-approved nasal spray for treatment-resistant depression and major depressive disorder with acute suicidal ideation. It works on the glutamate system rather than serotonin or norepinephrine, promoting neuroplasticity and producing antidepressant effects within hours to days rather than weeks.
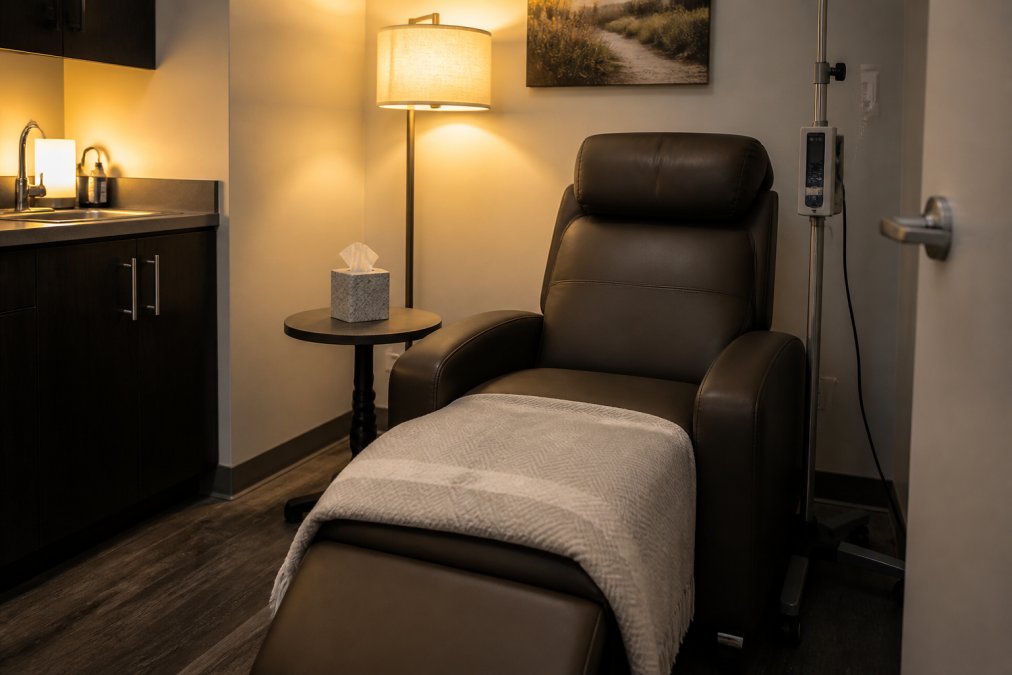
Esketamine is administered in a certified healthcare setting under clinical supervision. Patients remain at the clinic for approximately two hours after each dose to be monitored for dissociative effects and blood pressure changes. The treatment schedule typically begins with twice-weekly sessions, tapering to weekly and then biweekly as the patient stabilizes.
For patients who have not responded to multiple serotonin-targeting medications, a glutamate-targeting approach may work. Esketamine works best as part of a broader treatment plan that includes ongoing psychiatric support.
Salado Creek Mental Health offers after-hours Spravato services for patients who cannot take time away from work. Insurance coverage for esketamine varies significantly. Contact our team directly for guidance on what to expect for your situation.
According to the FDA’s prescribing information for Spravato, esketamine is only available through a restricted distribution program called the REMS program, which requires administration in a certified medical setting.
Esketamine is not appropriate for patients with uncontrolled hypertension, certain cardiovascular conditions, or active psychosis. A thorough medical evaluation is required before starting treatment. Never seek esketamine outside a certified clinical setting.
TMS Therapy for Depression: A Non-Invasive Neurostimulation Option
Transcranial magnetic stimulation (TMS) uses focused magnetic pulses to stimulate specific brain regions associated with mood regulation, primarily the left dorsolateral prefrontal cortex. It is FDA-cleared for major depressive disorder and requires no anesthesia, hospitalization, or recovery time.
A standard TMS course runs five sessions per week for four to six weeks. Each session takes 20 to 40 minutes, and patients can drive themselves home immediately afterward. The most common side effects are scalp discomfort and headache during or after sessions, which typically diminish over the first week.
TMS is particularly well-suited for patients who cannot tolerate medication side effects or who have had inadequate responses to pharmacotherapy. It is not appropriate for patients with metal implants in or near the head.
| Treatment | FDA Status | Setting | Typical Course | Common Side Effects |
|---|---|---|---|---|
| TMS | FDA-cleared | Outpatient | 4-6 weeks, 5x/week | Scalp discomfort, headache |
| Esketamine | FDA-approved | Certified clinic | Twice weekly, then tapering | Dissociation, nausea, dizziness |
| ECT | FDA-cleared | Hospital/outpatient | 3x/week, 2-4 weeks | Memory effects, confusion |
| VNS | FDA-approved | Implanted device | Ongoing | Hoarseness, cough |
| DBS | Investigational | Surgical | Ongoing | Surgical risks, mood shifts |
Other Evidence-Based Treatment Options for Resistant Depression
The treatment landscape extends well beyond medications and the options above. Several additional evidence-based approaches deserve serious consideration.
Electroconvulsive Therapy (ECT)
ECT is the most effective treatment available for severe, refractory depression, with a higher remission rate than any other single intervention. Modern ECT is performed under general anesthesia with muscle relaxants. The patient is unconscious during the procedure and experiences no pain. The primary side effect of concern is temporary memory disruption, which should be discussed honestly with your treatment team. For patients with severe, life-threatening depression who have not responded to other treatments, the risk-benefit calculation often favors ECT decisively.
ECT is typically considered after augmentation strategies have failed, though it may be moved earlier for patients with severe suicidality, psychotic features, or catatonia.
Vagus Nerve Stimulation and Deep Brain Stimulation
Vagus nerve stimulation (VNS) is FDA-approved for treatment-resistant depression in adults who have not responded to at least four adequate antidepressant treatments. A small device implanted under the skin near the collarbone delivers electrical pulses to the vagus nerve, modulating neurotransmitter activity in mood-regulating brain regions. Meaningful antidepressant effects often take six to twelve months to emerge.
Deep brain stimulation (DBS) for depression remains largely investigational. It involves surgically implanting electrodes in specific brain regions and is currently available primarily through clinical trials. According to ClinicalTrials.gov’s database of DBS depression studies, several trials are actively enrolling patients. DBS is not standard-of-care at this time but represents a meaningful avenue for patients who have exhausted all other approaches.
Psychotherapy: CBT, ACT, and Behavioral Activation
Psychotherapy is not a consolation prize when medications fail. For treatment-resistant depression, specific evidence-based modalities add meaningful benefit when combined with pharmacological or neurostimulation approaches.
- Cognitive behavioral therapy (CBT) targets distorted thinking patterns and behavioral avoidance that maintain depressive episodes.
- Acceptance and Commitment Therapy (ACT) shifts the goal from eliminating negative thoughts to reducing their behavioral impact.
- Behavioral activation targets the withdrawal and inactivity that perpetuate depression.
The multimodal approach, combining psychotherapy with pharmacotherapy or neurostimulation, consistently outperforms either modality alone.
A Patient-Centered Recovery Roadmap: From Evaluation to Maintenance
Most guides describe treatment options in isolation. Here is a practical framework for sequencing them.

Stage 1: Comprehensive Evaluation. A thorough psychiatric evaluation should document prior treatment trials, doses, durations, and reasons for discontinuation. Comorbid conditions should be screened and addressed. This stage often reveals that prior trials were inadequate, which changes the treatment algorithm significantly.
Stage 2: Augmentation. If prior antidepressant trials were adequate, augmentation with an evidence-based adjunctive agent is typically the next step.
Stage 3: Interventional Psychiatry. When augmentation fails, the pathway moves to esketamine, TMS, or ECT depending on the patient’s clinical profile, preferences, and access to care.
Stage 4: Maintenance. Achieving remission requires an ongoing plan to sustain it.
Building a Multimodal Treatment Plan
No single intervention is sufficient on its own. Patients who achieve remission through esketamine or TMS and then discontinue all other support are at high relapse risk. Effective treatment plans layer interventions: a neurostimulation approach combined with ongoing medication management and regular psychotherapy produces more durable outcomes.
A practical multimodal checklist:
- Document all prior medication trials with doses and durations
- Screen and treat comorbid conditions before labeling as TRD
- Establish a current medication regimen with clear augmentation rationale
- Identify the most appropriate neurostimulation or interventional option
- Enroll in evidence-based psychotherapy (CBT, ACT, or behavioral activation)
- Set a clear definition of treatment response and remission for this patient
- Schedule regular follow-up to monitor symptom severity and adjust the plan
Long-Term Maintenance Strategies and Relapse Prevention
Relapse prevention requires explicit planning. Many patients who achieve remission reduce their engagement with treatment precisely when they feel better, the highest-risk period.
Evidence-based maintenance strategies include:
- Continuing antidepressant medication at the therapeutic dose that produced remission, typically for at least one to two years after the first episode and indefinitely after multiple episodes
- Maintenance TMS therapy (monthly or quarterly sessions) for patients who responded to an acute TMS course
- Ongoing psychotherapy focused on relapse prevention skills and identifying early warning signs
- Regular psychiatric follow-up to monitor for symptom recurrence
The single most predictive factor for long-term recovery in resistant depression is whether the patient has an active, documented maintenance plan.
Caregiver Support and Resources for Families Navigating Refractory Depression
Refractory depression affects family members and caregivers significantly. They manage crises, navigate the healthcare system, and absorb the emotional weight of watching someone they love fail to respond to treatment after treatment.
What caregivers actually need:
Education about the condition. Understanding that TRD is a medical condition defined by treatment failure, not a failure of willpower, changes how caregivers respond and advocate. The National Alliance on Mental Illness family support resources offers structured education programs specifically designed for family members.
Boundaries and sustainability. Caregiver burnout is a clinical reality. A caregiver who is depleted cannot support a patient effectively. Establishing sustainable boundaries, including seeking their own mental health support, is essential for long-term caregiving.
Practical advocacy skills. Caregivers often notice early warning signs before the patient does. Teaching caregivers to document symptom changes, communicate clearly with the treatment team, and advocate for treatment escalation is a high-impact intervention.
Peer support. Connecting with other families navigating similar experiences reduces isolation. NAMI Family Support Groups and the Depression and Bipolar Support Alliance offer peer-led options.
| Recovery Stage | Key Actions | Who Is Involved |
|---|---|---|
| Evaluation | Document prior trials, screen comorbidities | Psychiatrist, patient |
| Augmentation | Add adjunctive agents, monitor adherence | Prescriber, patient |
| Interventional | TMS, esketamine, or ECT as appropriate | Specialist, prescriber |
| Psychotherapy | CBT, ACT, or behavioral activation | Therapist, patient |
| Maintenance | Ongoing medication, follow-up, relapse plan | Full care team, caregiver |
Resistant depression is one of the most complex challenges in psychiatry. Salado Creek Mental Health specializes in this kind of care: comprehensive psychiatric evaluation, medication management, access to after-hours Spravato services, and a patient-centered approach that treats the whole person. If you or someone you care about has been through multiple treatments without lasting relief, a complimentary phone consultation is a low-barrier first step. Make an appointment now and find out what a structured, individualized treatment plan actually looks like.
Frequently Asked Questions
What qualifies a patient for a diagnosis of treatment-resistant depression?
Treatment-resistant depression is generally defined as major depressive disorder that has not responded adequately to at least two different antidepressant medications, each taken at a therapeutic dose for a sufficient duration, typically six to eight weeks. A thorough psychiatric evaluation is essential before this label is applied, since factors like misdiagnosis, undertreated comorbid conditions, or poor treatment adherence can mimic treatment failure. A qualified psychiatrist reviews your full medication history before confirming the diagnosis.
What are the next steps when standard antidepressants don't work?
When standard antidepressants fail to provide relief, the next steps typically follow a structured treatment algorithm. Your psychiatrist may first try medication augmentation strategies, adding a second agent such as an atypical antipsychotic or lithium to your existing pharmacotherapy. If augmentation does not produce clinical remission, neurostimulation options like TMS therapy for depression or FDA-approved esketamine treatment for depression become appropriate considerations. Psychosocial interventions, including cognitive behavioral therapy, are usually added throughout this process to support patient outcomes.
How does esketamine treatment for depression differ from traditional antidepressants?
Traditional antidepressants primarily work by modulating monoamine neurotransmitters like serotonin and norepinephrine, and can take weeks to show effect. Esketamine, sold under the brand name Spravato, works through a different mechanism involving glutamate neurotransmitter modulation and neuroplasticity, and many patients report symptom improvement within hours to days of their first intravenous-style nasal spray session. It is FDA-approved specifically for treatment-resistant depression and is administered in a certified clinical setting under medical supervision.
Is treatment-resistant depression considered a chronic condition?
Resistant depression can follow a chronic course for some patients, but this does not mean improvement is impossible. Many people achieve significant symptom reduction or clinical remission with a multimodal approach that combines pharmacotherapy, neurostimulation, and psychotherapy. Long-term maintenance strategies, including ongoing medication management and relapse prevention planning, are a standard part of care. Regular psychiatric evaluation helps adjust the treatment plan as your needs change over time.
What role does psychotherapy play in managing resistant depression?
Psychotherapy is a core component of evidence-based care for resistant depression, not an optional add-on. Cognitive behavioral therapy helps patients identify and change thought patterns that sustain depressive symptoms. Acceptance and Commitment Therapy addresses psychological flexibility, while behavioral activation focuses on re-engaging with meaningful activities to improve mood. These approaches address psychosocial factors that medication alone cannot resolve, and research consistently shows better patient outcomes when therapy is combined with pharmacological or neurostimulation treatments.
Can caregivers and family members access support when a loved one has treatment-resistant depression?
Caregiver support is an often-overlooked part of the care picture. Family members dealing with a loved one's refractory depression frequently experience their own stress, grief, and burnout. Many psychiatric practices offer family psychoeducation sessions that explain the treatment process and set realistic expectations. National organizations such as NAMI (National Alliance on Mental Illness) provide free caregiver resources, support groups, and helplines. Encouraging caregivers to seek their own mental health support is a recognized part of a comprehensive, patient-centered care model.



